
Voters Reject Trump Administration’s Policies, Including Its Health Agenda
Election results put Medicaid cuts, Affordable Care Act subsidies and access to mental health care at the center of the healthcare debate.

Greetings, MindSite News readers.
It’s a rainy yet balmy November day in Michigan, and as the election results continue to roll in, I feel alright. My faith in this nation has been buffering since November 2024 as, like you, I navigate the world under governmental policies designed to make living harder.
But thanks to the millions of people who decided to vote, yesterday’s midterm elections reshaped Congress and the states. Health care was on the ballot, from Medicaid cuts to the MAHA movement, and voters vehemently rejected white Christian nationalism and Trumpism. Also today: why workers with long COVID are increasingly afraid to request the accommodations they’re owed and a critical care doctor’s case for studying psychedelics at the end of life.
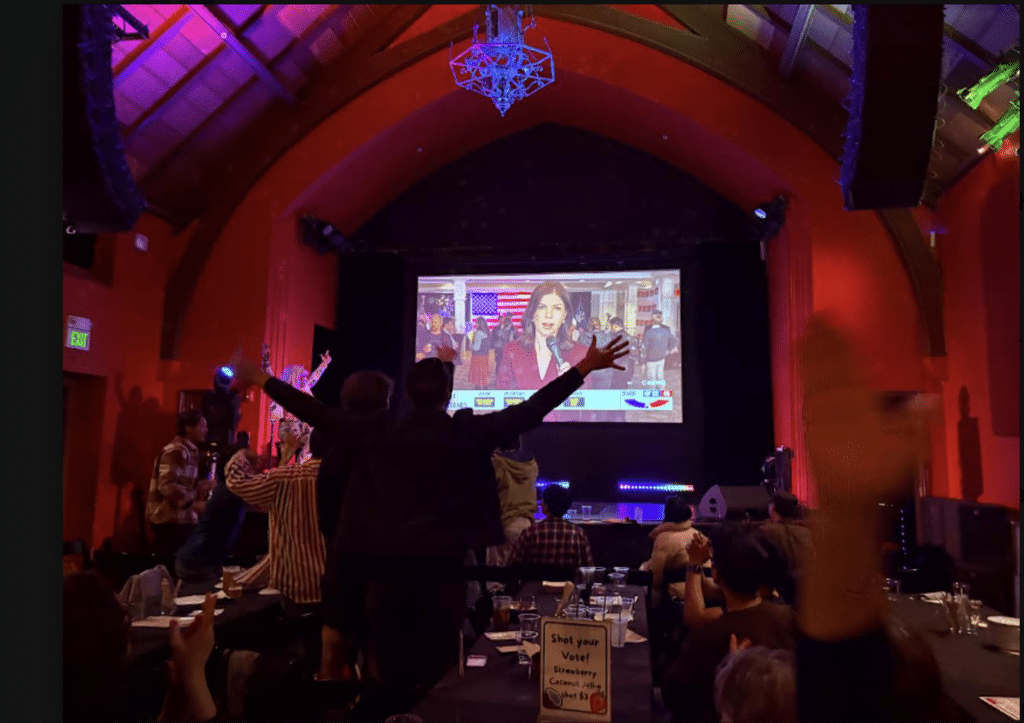
Photo: Laurie Udesky
Voters reject GOP’s health care agenda while doctors, scientists win key races
The overwhelming repudiation of Trump policies displayed by the results of yesterday’s election has many roots. Among them is a rejection of the administration’s authoritarianism and warmongering, its ICE shock troops and the soaring prices of everything from groceries to fuel. But the Democratic victory is also a powerful rebuke to the GOP’s health policies, including cutbacks to Medicaid and its approach to mental health.
As STAT News put it, “Republicans — who pushed sweeping, unprecedented health reforms, from Medicaid cuts to MAHA’s upheaval — had a terrible, no good, very bad election night on Tuesday.”
Some key candidates in the Make America Healthy Again (MAHA) movement, aligned with controversial Health Secretary Robert F. Kennedy, Jr., lost their elections, including Sen. Roger Marshall (R-Kansas), a founding member of the MAHA Caucus, and Iowa Republican gubernatorial candidate Zach Lahn.
Democratic candidates who promoted trust in science and had a science or healthcare background, on the other hand, did well last night. Physician Amy Acton, who led Ohio’s response to the COVID-19 pandemic, beat out Republican candidate Vivek Ramaswamy for the Ohio governorship. Her platform included forgiving medical debt, taking on “surprise” billing, making Medicaid more accessible and lowering prescription drug costs.
Pediatrician Annie Andrews of South Carolina and epidemiologist Abdul El-Sayed of Michigan, meanwhile, are the first Democrats with medical degrees to be elected to the Senate since 1969.
“My two decades as a physician have shown me in a thousand heartbreaking ways just how broken our health care system is,” Andrews said in her platform on reducing health care costs. Terming health care a “right” rather than a “privilege,” she vowed to maintain access to vaccines and work to prevent rural hospitals from closing, STAT added.
At the time of writing, Democrats have taken control of both chambers of Congress, winning at least 54 seats in the Senate and 234 in the House, with races in Alaska and Mississippi still pending. In their push for better healthcare, another STAT story reports, restoring Affordable Care Act subsidies and reversing Medicaid cuts will likely be Democrats’ first objectives. – Diana Hembree
For workers with long COVID, asking for help now feels like a risk
The COVID pandemic is associated with the largest number of registered disabilities for Americans since the Americans with Disabilities Act was passed in 1990, leaving millions to suffer from long COVID. Almost seven years have gone by and, in addition to bearing the stress of the illness, many also contend with the fear of asking their employers for necessary accommodations.
The Trump administration’s anti-worker and anti-disability policies, including the shuttering of the nation’s long COVID office by the Department of Health and Human Services in 2025, have left workers anxious and uncertain about requesting the workplace accommodations they’re legally owed through the ADA, Mother Jones reports. Corporate backlash and the spread of AI-powered “bossware” monitoring actions from keystrokes to bathroom breaks have only made the situation worse.
“Employers feel very comfortable undermining all these benefits,” said Barbara Comerford, a New Jersey-based lawyer who lives with myalgic encephalomyelitis/chronic fatigue syndrome. “I’ll get calls from lawyers who represent employers,” Comerford continued, “and they’re trying to get around some of the provisions that protect people…what they do is they look for a hardship basis to excuse having to accommodate people.” Filing disability insurance claims has become equally tough. The insurance industry “knows they’ve got a friend in the White House,” she said.
In 2021, President Biden announced that long COVID would be treated as a disability under federal law — guaranteeing reasonable accommodations at work for those affected. About 8 in 10 people with the condition can work with appropriate adjustments, one study found.
Even before Trump retook office, a 2024 report found that nearly half of disabled workers and job seekers who didn’t disclose their need for accommodations were afraid to ask for them. And in Trump’s term, employers have grown bolder about rejecting accommodations despite research showing that they improve retention and productivity. Going without accommodations is also costly: A University of Florida study published earlier this year estimated that lost jobs and work hours from long COVID totaled more than $12 billion in 2022 alone.
Moreover, having long COVID makes it harder to fight these workplace injustices. Symptoms and severity can vary widely and the illness is still poorly understood, which invites skepticism at work, said Doron Dorfman, a Seton Hall University law professor. The illness has also been politicized within an administration that downplays the virus, said California-based employment and disability attorney Hillary Benham-Baker. Altogether, very few long COVID cases make it to the Equal Employment Opportunity Commission, a Bloomberg Law analysis found, even as disability complaints expanded from under 23,000 in fiscal year 2021 to more than 36,000 in fiscal year 2025.
What comes next is uncertain. Comerford wants a more robust ADA that makes it harder to deny accommodations when employees complete their required work. But former Rep. Tony Coelho, the law’s primary author, has warned that debating it in today’s political climate could make circumstances worse. For now, Benham-Baker says, clearer guidance for employers could make a real difference, even if it only comes from the states.
More research should be done on psychedelics to treat the dying, one doctor says
Physicians are trained to provide treatments that cure illnesses and reduce suffering. But few tools help ease the existential fears that some terminally ill patients experience as they near death, Dr. Daniela Lamas writes in the New York Times. As a pulmonary and critical care physician at Brigham and Women’s Hospital in Boston, Lamas has seen that gap at the bedside. Describing the suffering and terror she witnessed in one patient whose cancer had spread to her bones, Lamas wondered whether she “could have done something more for her than to blunt her consciousness” with calming meds and sedatives.
While not quite ready yet, Lamas is optimistic about the small but growing body of research suggesting that psilocybin, the psychoactive compound in so-called magic mushrooms, can relieve the fear and hopelessness some people experience as they contend with death. By acting on the brain’s serotonin receptors, the drug produces several hours of altered perception and, for some, a lasting change in how they view and understand their own lives. Researchers believe it briefly relaxes the brain’s rigid habitual patterns, leaving patients more receptive to the therapy that accompanies it.
The Food and Drug Administration has finalized its guidance on how psychedelics should be studied and heard from the public on how they should be delivered. The agency could decide whether to approve psilocybin for treatment-resistant depression as soon as early 2027.
That’s good news for lots of people — except her critically ill and dying patients, Lamas writes. Psychedelic trials tend to enroll people who are medically stable, able to complete hours of preparatory therapy and remain available for weeks of follow-up. Moreover, the studies are nearly impossible to blind, because people who take psilocybin can tell that it isn’t a placebo. Patients who expect a life-changing experience or who get extra time with a therapist may feel better for those reasons alone. The drug has risks, too: some people have lasting anxiety after a trip, especially outside of a research setting.
Still, Lamas argues, those concerns are fundamentally different at the end of life. A dying patient seeks less terror and more meaning — something only the patient can judge. This makes rigorous study all the more vital. “If some of the benefit comes from the attention, the sense that someone is trying to help, those are important data,” she writes, urging the regulators and health officials shaping policy to consider whether and how psychedelic treatments can benefit hospitalized patients, too.
In other news…
Brain Stories Connections: Inspired by her own horrifying experiences in psychiatric hospitals as a teen and young adult, Washington University professor of public health Morgan Shields now studies how infrequently these facilities are held accountable for providing poor care. That’s by design, with a system built around managing risk and money, not recovery or human rights, Shields explained on the latest episode of Brain Stories Connections. For years, inpatient psychiatric care was the only hospital setting left out of federal patient-experience surveys, a gap the Centers for Medicare & Medicaid Services only began closing this year. Shields calls that care “an example of profound betrayal by our healthcare system” and points instead to Trieste, Italy, where open-door, restraint-free care built on long-term trust offers a different model.
In a workplace tragedy, the hardest part can come later: Safety professionals know the workplace emergency protocol: Call 911, give first aid, notify managers and regulators, open an investigation. But once that’s done, the emotional fallout for workers, both immediately and over the long term, can slip through the cracks, Safety+Health reports. Employee reactions vary and some don’t surface for days or weeks said Emily Haas of the National Institute for Occupational Safety and Health. Workers in high-risk jobs are also used to functioning under pressure, so distress may be hard to detect even as exhaustion and preoccupation cut into focus on dangerous worksites. That’s why Haas urges managers to keep checking in long after the investigation wraps. “Everyone experiences, progresses and recovers on a different timeline,” Haas said. “It’s easy and natural for us to address something right away and then move on. [But] when you have a traumatic incident or experience, it’s not a checklist.”
The name “MindSite News” is used with the express permission of Mindsight Institute, an educational organization offering online learning and in-person workshops in the field of mental health and wellbeing. MindSite News and Mindsight Institute are separate, unaffiliated entities that are aligned in making science accessible and promoting mental health globally.


Author

Related Articles

Who’s Paying for California’s Crisis Care?
California counties say insurers are failing to cover mobile mental health crisis teams, leaving taxpayers with millions in unpaid bills.

Helping Trick-Or-Treaters With Autism Feel Welcome
This year, make Halloween more inclusive for autistic children with these six tips for welcoming neurodivergent trick-or-treaters.

How AI Is Erasing Our Core Relationships
Researchers warn that AI chatbots may contribute to loneliness and social isolation by replacing human relationships, calling for better oversight and research.